Arm Liposuction Clinics: Why Do Results Diverge?

It is the same procedure by name, yet the accounts of results are all over the place. Read through reviews and satisfied posts sit right beside disappointed ones, until it starts to feel like a matter of luck.
It is not luck. Results are not settled in the operating room alone; a substantial part of them diverges from what was checked beforehand and what was decided in advance. The four points below are where that happens.
Same procedure, so why do results differ?
The arm varies more than other areas. The reason is structural.
The abdomen has a thick fat layer, which gives some margin. Remove a little more or a little less and the surface absorbs the difference. The arm is the opposite. The fat layer is thin and so is the skin, so a difference of a few millimeters shows directly on the surface. The less margin an area has, the more directly a difference in judgment becomes a difference in result.
So on the arm, judgment determines the result more than instruments do. There are four places where that judgment is made.
| Point of divergence | When it was checked | When it was not |
|---|---|---|
| Layer assessment | Enters knowing whether the fat is superficial or deep | Starts from pinched thickness alone |
| Thickness to leave | Decided in advance and stopped at that line | Removes as much as can be removed |
| Treated area | Sets where to stop after assessing the connecting zones | Stops at the arm because it is called arm surgery |
| Follow-up | The people who know the starting state follow the course | Reviewed from handed-over records |
The right-hand column is not wrong as such. But the further right you go, the more the result swings with conditions.

Were the fat layers assessed beforehand?
The first point. Fat at the back of the arm is not one mass but divides into a superficial and a deep layer.
The two layers behave differently. The superficial layer sits just beneath the skin, so removing a lot from it leaves the surface uneven. The deep layer lies closer to the fascia and has relatively more margin. At the same thickness, where and how much to remove changes with which layer the fat is concentrated in.
This distinction does not come out by hand. A thick pinch tells you there is fat somewhere, but not whether it is above or below. The layers separate only under ultrasound.
Whether edema is mixed in has to be assessed alongside. Counting edema as fat leads to overestimating the volume to remove, and then you cut into the thickness that should have been left. What to check and what to ask in a consultation is set out on the Pre-Surgery Examination page.
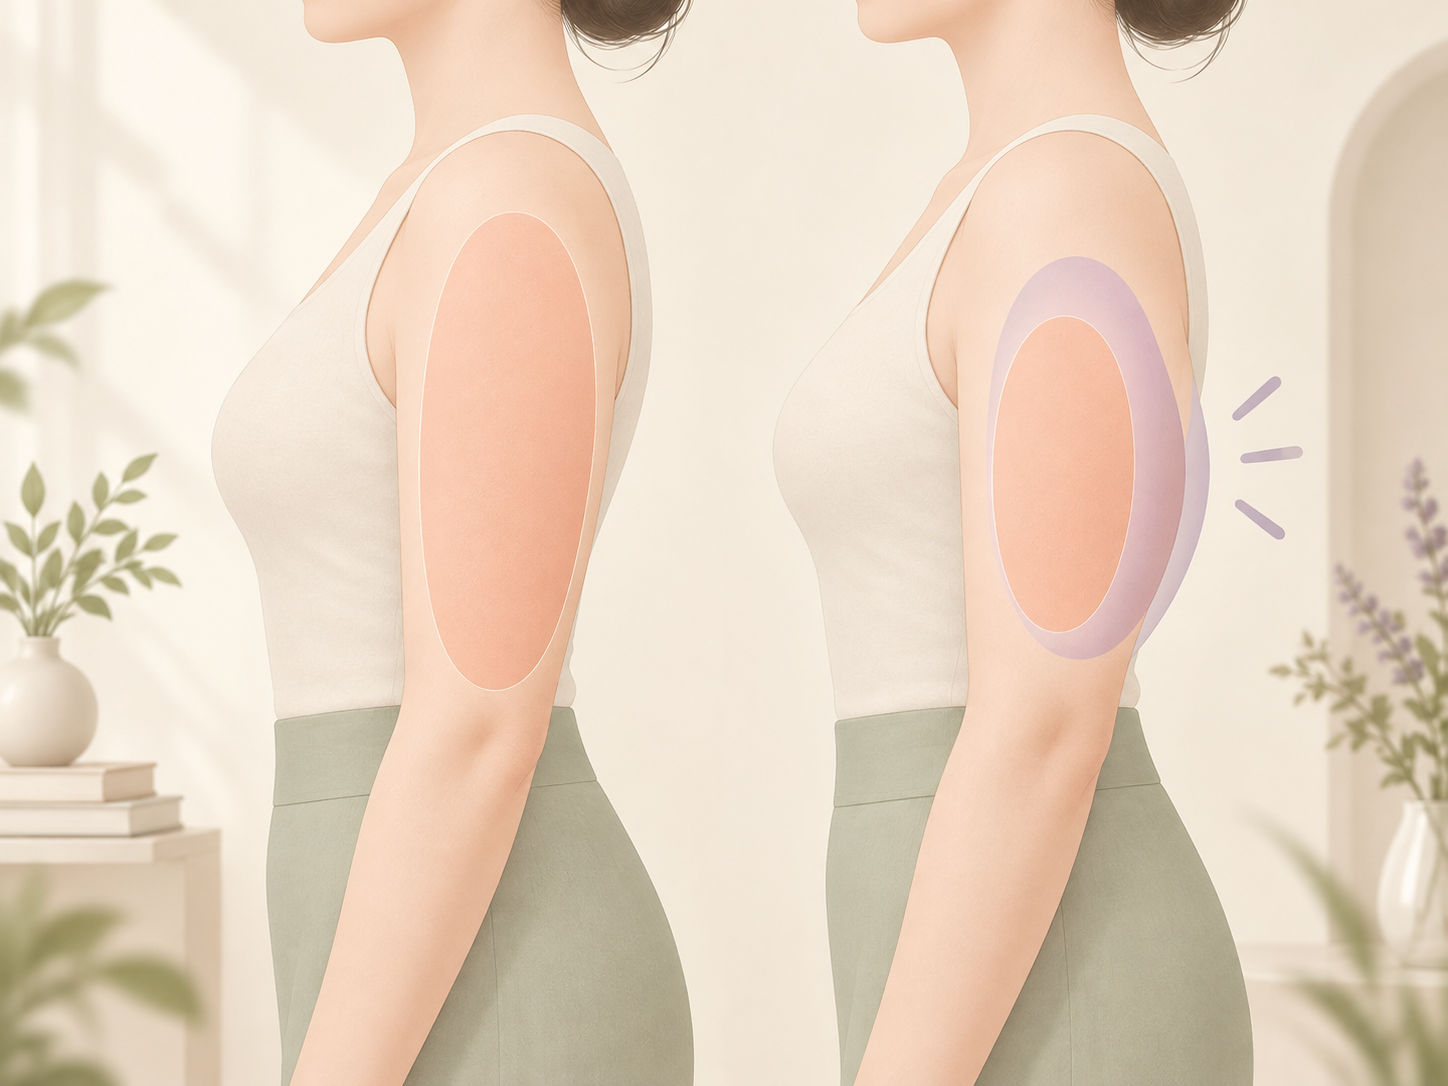
Was the thickness to leave decided in advance?
The second point, and one that divides results considerably.
Fat is not only something to be removed. It is the layer that supports the surface from beneath the skin, so a certain amount must remain for the line to run smoothly. Start without setting the thickness to leave and the standard becomes “as much as can be removed,” which on an area with as little margin as the arm readily produces an uneven surface.
On an arm with low elasticity this problem lands harder. Once the supporting volume is gone, the leftover skin is exposed as it is, and you end up thinner but with the sag more noticeable when the arm is raised. So the weaker the elasticity, the more conservatively we set the thickness to leave.
Setting it in advance keeps the standard in place during surgery too. Without it, the judgment gets made on the spot, and that opens room for the two sides to come out differently.
Where was the treated area cut off?
The third point. There is a reason arm liposuction does not end at the arm.
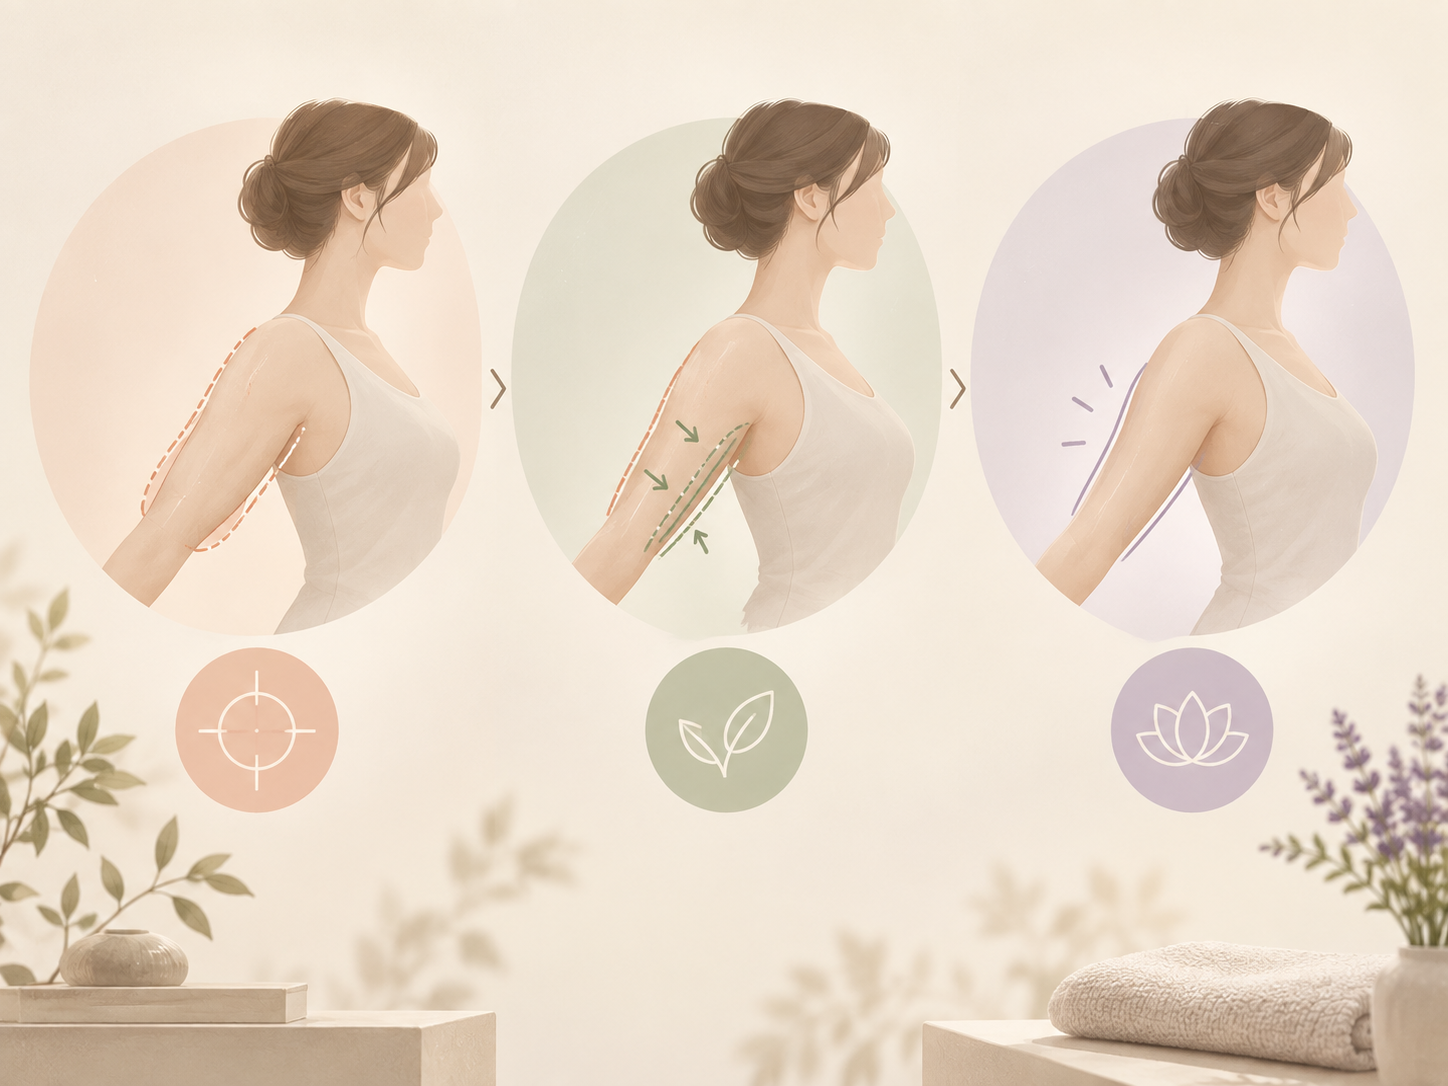
Fat at the back of the arm forms one line with the front fold of the armpit, the accessory breast, and the rear running into the bra line. Accessory breast is the common term, though not a precise one; it refers to the fat that bulges at the front of the armpit. Treat the arm alone and leave the connecting zones and a line that was not there before can form between them. This is where the arm becomes slimmer while the silhouette from behind stays as it was.
So when setting the area, we look at the arm lowered and raised separately, then work through whether the front of the armpit folds, whether the accessory breast protrudes, and whether there is thickness running into the bra line. When several of these show together, extending the area gives a smoother result than treating the arm alone.
Conversely, some arms need only the arm. If the connecting zones are clean, there is no reason to widen. What matters is not whether the area is wide but whether the stopping point was set after assessing the arm.
One more thing attaches here: following the course. Ambiguous states come up often during recovery — one side feeling harder at week three, firmness persisting at month two. Telling whether that is a common course or warrants a look requires knowing the starting state. Someone who knows which layers were addressed and how much asymmetry was there originally judges it faster. The result does not end with surgery; it runs through this stretch as well.
When results differ within the same clinic
One more point. Results diverge not only between clinics but within the same one.
The biggest variable is patient condition. With different fat layer thickness, skin elasticity, and recovery speed, the same plan produces different results. So good reviews do not mean the same result on your arm. What to look for in a review is not the size of the result but whether that person’s conditions resemble yours.
Review counts work the same way. A high count means a lot of procedures were done, not that they suit your arm. It is better to look by body area, and how many arm cases there are means more than the total. Extensive experience with the abdomen does not transfer directly to the arm, because the two differ in fat layer thickness and skin margin, which makes the very basis for judgment different.

Four reasons volume removed and device names are not answers
The last point. These are the two items people compare most when choosing a clinic, and neither explains the result.
First, the same volume differs by which layer it came from. Removed from the superficial layer and removed from the deep layer read entirely differently on the surface, even at identical volume.
Second, removing a lot is not the same as removing well. The arm has little margin, so it is not an area where more is better. Read a larger number as better and the direction reverses.
Third, a device is a tool, and tools do not decide where to stop. The way fat is broken up or suctioned may differ, but which layer to stop at and how much to leave is a human judgment. It is why results diverge even among clinics using the same device.
Fourth, neither number can be verified before surgery. The estimated volume you hear in consultation differs from the actual, and device specifications do not connect to your arm. Whether the layers were assessed and whether the thickness to leave was set, by contrast, are things you can ask directly in consultation.
What to look at first is not the numbers but the process that sets them. It divides on whether the consultation explains what your arm’s layers look like and where the plan leaves thickness, or leads with how much can be removed. How to narrow the field, and in what order, is covered on the Arm Liposuction page.
What can be verified before surgery ends here. Whether the layers were assessed, whether the thickness to leave was set, and where the area will be cut off are all things you can ask about and get answers to in consultation. Volume removed and device specifications cannot be checked in advance, so choosing on the side that cannot answer while leaving the side that can unasked inverts the order. If the answers to those three questions come back as generalities rather than as statements about your arm, then no amount of volume or device quality will let you picture the result beforehand.
Whether the layers were assessed, whether the thickness to leave was set, and where the area will be cut off are items you can raise directly in consultation. At Line Culture Clinic we measure the layers with ultrasound and set the thickness to leave together, precisely so the answer comes to you as a process rather than a number. If you are comparing clinics, put the same three questions to them, and if you want the answers for your own arm, come and check in consultation.